
Read next
One high reading is not a diagnosis. Learn how pediatric blood pressure is confirmed, which risks matter, and when to seek medical care.
What does a high blood pressure reading at a school screening mean?
A single high blood pressure reading in a child or adolescent does not confirm hypertension; it means the measurement should be repeated correctly and interpreted according to age, sex, and height when applicable123. Population screening has limitations, and a result above the expected range requires clinical confirmation4. A hypertension-range blood pressure reading at a single encounter is therefore a screening finding, not a diagnosis, and results from local school samples should not be extrapolated to all Brazilian children154. A 2019 meta-analysis of 47 studies involving 186,630 participants estimated the global prevalence of pediatric hypertension at approximately 4%, with variation according to measurement protocols and diagnostic criteria5.
How should blood pressure be measured in children and adolescents?
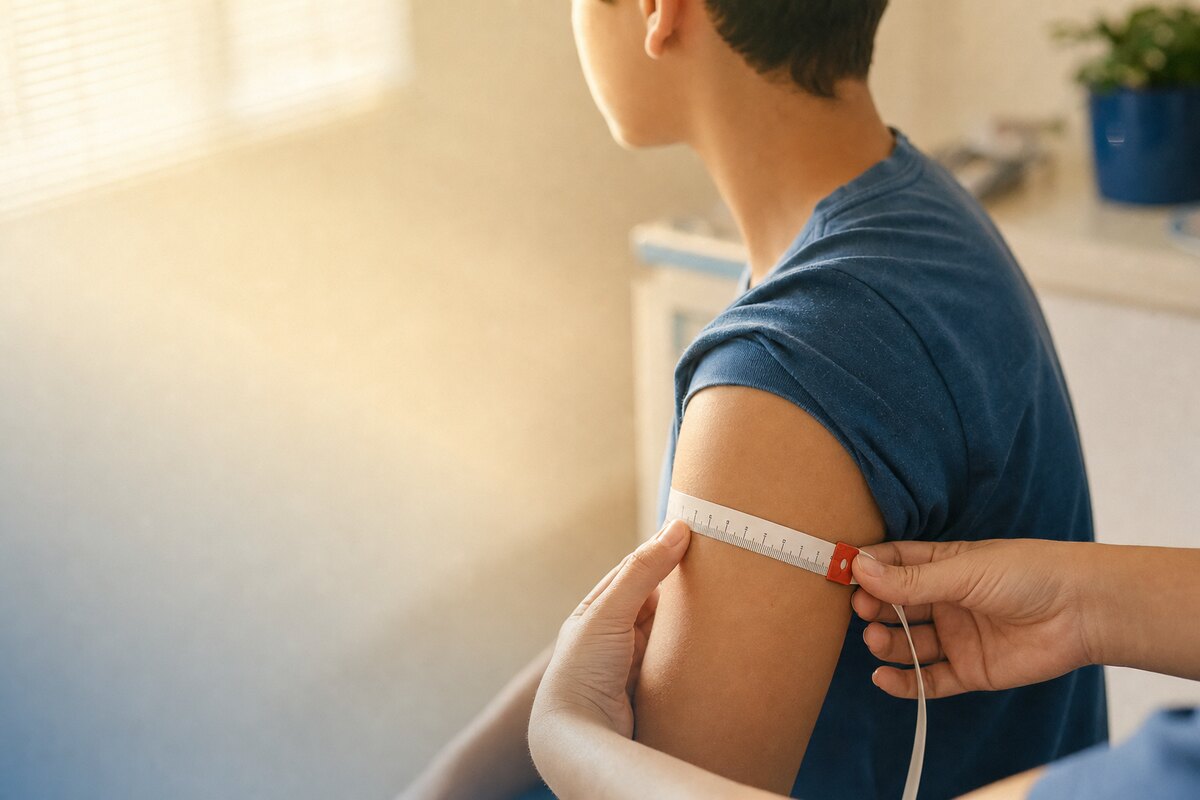
Reliable pediatric blood pressure measurement requires proper preparation, positioning, equipment, and cuff size123. Exercise, caffeine, food, and smoking should be avoided for 30 minutes beforehand, followed by three to five minutes of quiet rest without talking. The child or teenager should sit with the back supported, legs uncrossed, and feet supported. The measurement should preferably be taken on the bare right upper arm, supported at heart level, with an upper-arm device validated for pediatric use123. Anxiety, crying, pain, recent activity, and talking can temporarily raise the reading. The cuff’s inflatable bladder should cover 80% to 100% of the arm circumference and have a width close to 40%. A cuff that is too small tends to overestimate blood pressure, particularly in children and adolescents with obesity who may need larger sizes123. Three readings should be obtained one to three minutes apart, using the average of the last two. If an automated device shows a reading in the hypertension range, the result should be confirmed by an auscultatory, stethoscope-based measurement. Wrist or forearm monitors, unvalidated devices, and measurements taken over clothing should not be used to establish a diagnosis12.
How is pediatric hypertension confirmed and classified?
In the usual outpatient setting and in the absence of warning signs, diagnosis generally requires auscultatory confirmation at three separate visits1. Stage 2 readings, symptoms, or suspected hypertensive emergency require earlier assessment and may demand action before the third visit. In children younger than 13, readings are compared with reference tables for age, sex, and height percentile; hypertension generally means blood pressure at or above the 95th percentile on separate visits. From age 13 onward, normal blood pressure means SBP below 120 mmHg and DBP below 80 mmHg; elevated BP: SBP 120–129 mmHg and DBP <80 mmHg; stage 1: SBP 130–139 mmHg or DBP 80–89 mmHg; stage 2: SBP ≥140 mmHg or DBP ≥90 mmHg, using the higher category1. Any high reading should be repeated correctly during the same appointment; if it remains above the expected range, a pediatrician should interpret it individually123.
When does high blood pressure require prompt or emergency care?
Repeated readings in the stage 2 hypertension range require prompt reassessment even when the child has no symptoms3. For an asymptomatic patient, the American Academy of Pediatrics guideline recommends repeating the measurement or arranging specialist assessment within one week. Very high blood pressure with symptoms, a reading more than 30 mmHg above the 95th percentile, or blood pressure above 180/120 mmHg in an adolescent warrants immediate evaluation in an emergency department3. These figures are operational criteria for healthcare professionals, not thresholds for families to use for self-management. Acute neurological or cardiopulmonary symptoms associated with very high blood pressure are warning signs because a pediatric hypertensive crisis may cause encephalopathy, acute kidney injury, or heart failure3. If a child appears acutely unwell, in-person medical assessment should not be delayed.
Which risk factors should be assessed?
Primary hypertension has become more common in adolescents and is strongly associated with overweight and obesity, whereas secondary causes are more likely in young children or in patients with more severe blood pressure elevation1. In a global meta-analysis, hypertension was substantially more frequent among participants with obesity or overweight than among those considered to have a normal weight, although estimates varied across studies5. Other relevant factors include physical inactivity, a poor-quality diet, kidney disease, diabetes, obstructive sleep apnea, prematurity, aortic coarctation, medications that increase blood pressure, and certain endocrine or genetic conditions1. Clinical assessment should review perinatal history, growth, weight, diet, physical activity, sleep, family history, medications, and possible kidney, heart, or endocrine disease. Blood pressure should be measured annually from age three. Earlier measurement is particularly important after prematurity, very low birth weight, intrauterine growth restriction, neonatal intensive care, umbilical catheterization, congenital heart disease, kidney disease, urinary abnormalities, diabetes, transplantation, cancer treatment, or long-term use of medication associated with hypertension1. Depending on individual risk, measurement may be appropriate at every clinical visit12.
When are ambulatory monitoring and treatment needed?
Ambulatory Blood Pressure Monitoring, or ABPM, records blood pressure for about 24 hours while the patient is awake and asleep, helping identify sustained hypertension, white-coat hypertension, masked hypertension, and abnormal nighttime patterns162. Pediatric guidelines recommend ABPM to confirm hypertension after stage 1 readings at three visits or when elevated blood pressure persists for at least one year. Pediatric reference values and a validated device must be used1. Home readings may complement follow-up but should not replace medical assessment or ABPM when it is indicated12. Lifestyle measures are recommended for every child with blood pressure above the normal range, including weight management when needed, regular physical activity, less sedentary time, more minimally processed foods, fruits and vegetables, less sodium and ultra-processed food, adequate sleep, and stress management1. Medication is not prescribed because of one high reading. It is mainly considered for symptomatic hypertension, stage 2 hypertension without an evident modifiable cause, target-organ damage, or persistent hypertension despite non-drug measures1. Established pediatric hypertension can affect blood vessels, the retina, and the heart. Left ventricular hypertrophy has been reported in up to 40% of patients at initial diagnosis, but this figure comes from clinical populations and must not be applied to children identified only through school screening1.
What questions do families commonly ask, and what are the references and informational notice?
A high screening result deserves attention, but it should not cause panic or lead to medication without medical advice123. Question: does the absence of a headache rule out hypertension? No. Pediatric hypertension may remain completely asymptomatic1. Question: can blood pressure be monitored at home? Yes, as a supplement, using a validated upper-arm monitor, the correct cuff, and professional guidance; home readings do not replace medical evaluation or ABPM when required12. Question: what should happen after a high reading? Repeat the measurement correctly during the same visit and, if it remains high, arrange an assessment with a pediatrician. Depending on the findings, pediatric cardiology or nephrology evaluation and additional tests may be appropriate. Every result must be considered alongside the child’s growth, symptoms, medical history, and risk factors. References:1 Barroso WKS, Rodrigues CIS, Bortolotto LA, et al.; Brazilian Society of Cardiology. Diretrizes Brasileiras de Hipertensão Arterial – 2020 [Brazilian Guidelines of Hypertension – 2020]. Arquivos Brasileiros de Cardiologia. 2021;116(3):516–658. Version: 2020 guideline, published in 2021. DOI: https://doi.org/10.36660/abc.20201238.6 Flynn JT, Urbina EM, Brady TM, et al.; American Heart Association. Ambulatory Blood Pressure Monitoring in Children and Adolescents: 2022 Update: A Scientific Statement From the American Heart Association. Hypertension. 2022;79(7):e114–e124. Version: 2022 update. DOI: https://doi.org/10.1161/HYP.0000000000000215.2 Lurbe E, Agabiti-Rosei E, Cruickshank JK, et al.; European Society of Hypertension. 2016 European Society of Hypertension Guidelines for the Management of High Blood Pressure in Children and Adolescents. Journal of Hypertension. 2016;34(10):1887–1920. Version: 2016 guideline. DOI: https://doi.org/10.1097/HJH.0000000000001039.5 Song P, Zhang Y, Yu J, Zha M, Zhu Y, Rahimi K, Rudan I. Global Prevalence of Hypertension in Children: A Systematic Review and Meta-analysis. JAMA Pediatrics. 2019;173(12):1154–1163. DOI: https://doi.org/10.1001/jamapediatrics.2019.3310.4 US Preventive Services Task Force. Screening for High Blood Pressure in Children and Adolescents: US Preventive Services Task Force Recommendation Statement. JAMA. 2020;324(18):1878–1883. Version: 2020 recommendation statement. DOI: https://doi.org/10.1001/jama.2020.20122.3 Flynn JT, Kaelber DC, Baker-Smith CM, et al.; American Academy of Pediatrics Subcommittee on Screening and Management of High Blood Pressure in Children. Clinical Practice Guideline for Screening and Management of High Blood Pressure in Children and Adolescents. Pediatrics. 2017;140(3):e20171904. Version: 2017 clinical practice guideline. DOI: https://doi.org/10.1542/peds.2017-1904. This content is for information and education only and does not replace an individual medical consultation.
Sources
- 1.Diretriz Brasileira de Hipertensão Arterial – 2025 — Arquivos Brasileiros de Cardiologia; realização conjunta da Sociedade Brasileira de Cardiologia, Sociedade Brasileira de Hipertensão e Sociedade Brasileira de Nefrologia, 2025
- 2.Joint statement for assessing and managing high blood pressure in children and adolescents: Chapter 1. How to correctly measure blood pressure in children and adolescents — Frontiers in Pediatrics; iniciativa HyperChildNET/European Academy of Paediatrics, 2023
- 3.Clinical Practice Guideline for Screening and Management of High Blood Pressure in Children and Adolescents — American Academy of Pediatrics — Pediatrics, 2017
- 4.Pressão alta atinge três em cada 10 crianças em escolas brasileiras — Metrópoles, 2026
- 5.Global Prevalence of Hypertension in Children and Adolescents Younger Than 19 Years: A Systematic Review and Meta-Analysis — JAMA Pediatrics, 2025
- 6.Ambulatory Blood Pressure Monitoring in Children and Adolescents: 2022 Update: A Scientific Statement From the American Heart Association — American Heart Association, 2022
